
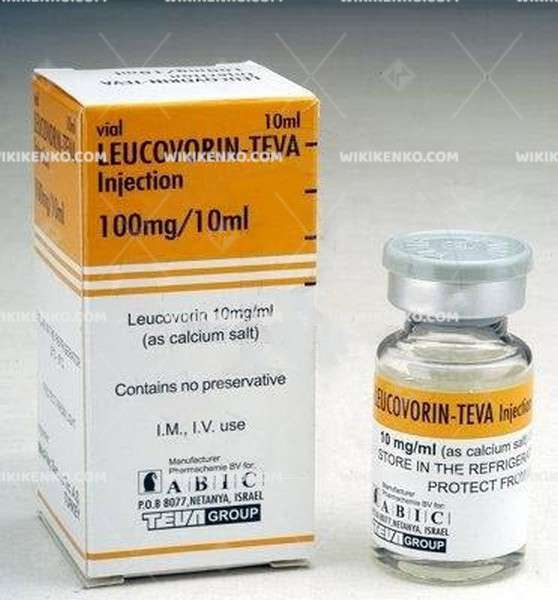
Description
Pharmaceutical composition and formulation
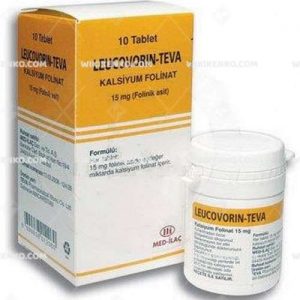
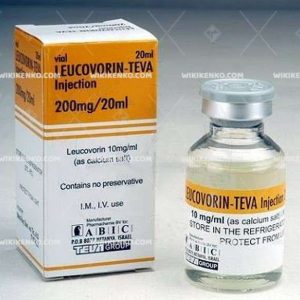
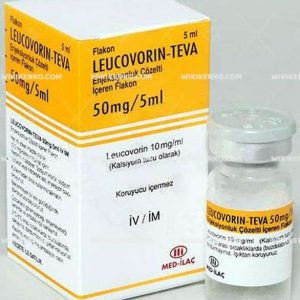
Each millilitre of Leucovorin‑Teva 10 mg/mL contains folinic acid 10 mg, present as calcium folinate, corresponding to a 100 mg total folinic acid content per 10 mL vial. The product is supplied as a clear yellow sterile solution for IV or IM use, with sodium chloride and water for injections as main excipients and small amounts of sodium per mL. The pH is adjusted with sodium hydroxide and hydrochloric acid, and the solution must be visually inspected for particulate matter and discoloration before administration.
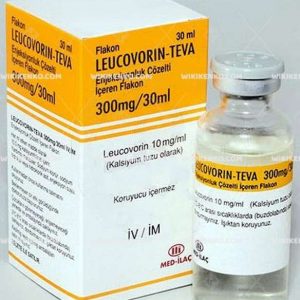
Leucovorin‑Teva is available in multiple vial sizes (e.g. 5, 10, 20, 30, 50 mL) all at a concentration of 10 mg/mL folinic acid, intended for single‑use in infusion preparation. For intravenous infusion, the concentrate may be diluted with 0.9% sodium chloride or 5% glucose, and the diluted solution is chemically and physically stable for up to 24 hours at 2–8 °C at concentrations between 0.06 and 1 mg/mL.
Pharmacological classification and mechanism of action
Folinic acid (leucovorin) is the 5‑formyl derivative of tetrahydrofolic acid and is classified as a reduced folate and antidote to folic acid antagonists. Unlike folic acid, folinic acid does not require dihydrofolate reductase for conversion to tetrahydrofolate coenzymes and thus bypasses methotrexate‑mediated inhibition of this enzyme. Intracellularly, it is converted to 5,10‑methylenetetrahydrofolate, which participates in thymidylate and purine synthesis and supports DNA replication and repair.
In combination therapy with 5‑FU, folinic acid stabilizes the ternary complex between thymidylate synthase, FdUMP (a 5‑FU metabolite), and reduced folate, thereby potentiating inhibition of thymidylate synthase and enhancing antitumour activity. In folate‑deficiency megaloblastic anaemia, folinic acid replenishes reduced folate pools, correcting impaired thymidylate synthesis and abnormal erythropoiesis, though it may mask vitamin B12 deficiency.
Therapeutic indications
Evidence‑based and regulatory documents support the following main indications for injectable calcium folinate/leucovorin products such as Leucovorin‑Teva:
-
Diminution of toxicity and antagonism of the effects of folic acid antagonists (particularly high‑dose methotrexate) in cytotoxic therapy (“leucovorin rescue”).
-
Use as a modulator of 5‑fluorouracil in the treatment of advanced or metastatic colorectal carcinoma.
-
Treatment or prevention of folate‑deficiency megaloblastic anaemia when oral therapy is not feasible or not appropriate, provided vitamin B12 deficiency has been excluded.
Off‑label or less common uses include modulation of other antifolate regimens and use in selected cases of accidental folate antagonist overdose, according to institutional protocols.
Posology and method of administration
General principles
Posology must follow the specific cytotoxic protocol, taking into account dose, timing and route of the folic acid antagonist and the patient’s renal function and methotrexate plasma levels. Leucovorin‑Teva may be administered intravenously (bolus or infusion) or intramuscularly; intrathecal administration is contraindicated. Because of the calcium load, no more than 160 mg leucovorin (16 mL of a 10 mg/mL solution) should be injected intravenously per minute.
Methotrexate rescue (illustrative protocols)
High‑dose methotrexate regimens typically start folinic acid rescue 24 hours after the beginning of methotrexate infusion. A commonly cited schedule is 15 mg (approximately 10 mg/m²) every 6 hours for 10 doses, adjusted according to methotrexate serum concentrations and renal function. For delayed methotrexate elimination or acute kidney injury, higher doses of leucovorin, for example 100 mg/m² IV every 3 hours, may be required until plasma methotrexate falls below 10⁻⁸ mol/L.
Leucovorin rescue must not be delayed beyond 24 hours post methotrexate and should continue as long as toxic methotrexate levels are present. Hydration, urine alkalinisation and close therapeutic drug monitoring are mandatory adjuncts to rescue treatment.
Modulation of 5‑fluorouracil in colorectal cancer
Several evidence‑based regimens for advanced colorectal cancer combine leucovorin with 5‑FU:
-
“Monthly” regimen: calcium folinate 20 mg/m² IV bolus or 200–500 mg/m² as 2‑hour IV infusion, followed immediately by 5‑FU 425 or 370 mg/m² IV bolus once daily for 5 consecutive days, repeated every 4 weeks.
-
“Weekly” regimen: calcium folinate 20 mg/m² IV bolus or 200–500 mg/m² as 2‑hour IV infusion, plus 5‑FU 500 mg/m² IV bolus administered during or at the end of folinate infusion.
Leucovorin and 5‑FU must not be mixed in the same syringe or infusion bag because of potential precipitation; they should be administered sequentially via separate lines or flushes.
Folate‑deficiency megaloblastic anaemia
In folate‑deficiency megaloblastic anaemia, parenteral dosing is typically up to 1 mg daily IV or IM in adults, with lower doses used in children, before switching to oral therapy when feasible. Careful diagnostic work‑up is necessary to exclude vitamin B12 deficiency, because folinic acid may correct haematologic parameters while allowing neurological damage to progress.
Pharmacokinetics
After IV administration of folinic acid, peak plasma concentrations are achieved immediately, whereas IM administration leads to slightly delayed but comparable exposure. Folinic acid is rapidly converted to active reduced folate metabolites, including 5‑methyltetrahydrofolate, which distribute widely into tissues and cerebrospinal fluid to a limited extent. The apparent plasma half‑life of folinic acid is short (in the order of tens of minutes), while downstream reduced folate metabolites exhibit longer half‑lives.
Folinic acid and its metabolites are eliminated primarily by renal excretion, through glomerular filtration and tubular secretion, with a minor biliary component. Significant renal impairment can result in accumulation of methotrexate and its metabolites rather than folinic acid itself, thus necessitating higher‑intensity rescue dosing and prolonged administration.
Contraindications and major warnings
Leucovorin‑Teva is contraindicated in patients with hypersensitivity to folinic acid, calcium folinate, or any excipient. It must not be used in pernicious anaemia or other megaloblastic anaemias due to vitamin B12 deficiency, because haematologic remission may mask irreversible neurological complications. Intrathecal administration of leucovorin is strictly contraindicated and has been associated with fatal outcomes when erroneously given this way.
Concomitant use with high‑dose methotrexate should follow established protocols; simultaneous administration in the same infusion without timing separation may reduce methotrexate’s antineoplastic activity. In 5‑FU combinations, folinic acid amplifies the toxicity of 5‑FU, making close monitoring of gastrointestinal, haematologic and mucosal adverse effects essential; if severe toxicity occurs, 5‑FU and folinic acid must be discontinued.
Adverse effects
Overview
Parenteral leucovorin is generally well tolerated when used as rescue therapy, but adverse reactions may arise from the drug itself and from its interaction with chemotherapy. Reported reactions include gastrointestinal, neurological, dermatologic and hypersensitivity events, with severity and frequency influenced by concomitant agents, particularly 5‑FU.
Representative adverse reactions
Common or clinically important adverse effects include:
-
Gastrointestinal: nausea, vomiting, diarrhoea, oral mucositis/stomatitis (especially with 5‑FU).
-
Haematologic (primarily with 5‑FU combinations): leukopenia, neutropenia, thrombocytopenia.
-
Neurological: insomnia, agitation; masking of B12‑deficiency‑related neuropathy.
-
Hypersensitivity: rash, pruritus, urticaria, anaphylactoid or anaphylactic reactions, including bronchospasm and hypotension.
-
Local: injection‑site pain or irritation with IV/IM administration.
Drug interactions
Folinic acid reduces the toxicity but may also attenuate the antitumour effect of folic acid antagonists if given inappropriately, for example if started too early or at excessively high doses relative to methotrexate. Conversely, in combination with 5‑FU, leucovorin enhances antimetabolite activity and toxicity by stabilizing the thymidylate synthase–FdUMP complex. Large doses of folates can reduce serum levels and effectiveness of antiepileptic drugs such as phenobarbital, phenytoin and primidone, potentially increasing seizure frequency.
Special populations and precautions
In patients with renal impairment receiving high‑dose methotrexate, delayed methotrexate clearance requires escalation and prolongation of leucovorin rescue and intensified supportive care. In elderly or frail patients receiving 5‑FU plus folinic acid, starting doses of 5‑FU must be reduced and carefully titrated because of increased susceptibility to severe mucosal and haematologic toxicity. In pregnancy, leucovorin is generally used only when clearly indicated (e.g. to treat methotrexate toxicity), and risk–benefit assessment is case‑specific.
In breastfeeding, data are limited; many guidelines recommend caution or temporary interruption of breastfeeding when leucovorin is used with cytotoxic agents such as methotrexate or 5‑FU. In paediatric patients, dosing principles mirror adult protocols but must be adjusted on a mg/m² basis, with vigilant monitoring of methotrexate levels and clinical status.
Storage, handling and compatibility
Undiluted Leucovorin‑Teva vials should be stored refrigerated at 2–8 °C and protected from light, in accordance with local product labelling. After dilution with compatible solutions such as 0.9% sodium chloride, 5% glucose, lactated Ringer’s or dextrose 10% in water, the product remains chemically and physically stable for up to 24 hours at refrigerated temperatures, although microbiological considerations may limit in‑use time. The solution should be used only if visually clear and free from particles, and any unused remainder must be discarded, as single‑use vials are intended.
Leucovorin‑containing solutions must not be mixed with 5‑FU or other drugs in the same infusion container due to risk of precipitation or incompatibility. Because of the calcium content, the IV injection rate must not exceed 160 mg/min to avoid potential cardiovascular complications related to rapid calcium loading.
Representative clinical and regulatory data
The following table synthesises key, evidence‑based information relevant to Leucovorin‑Teva 10 mg/mL and comparable calcium folinate injection products:
| Parameter | Evidence‑based information | Source |
|---|---|---|
| Active substance | Folinic acid 10 mg/mL as calcium folinate (reduced folate) | |
| Pharmaceutical form | Clear yellow solution for injection/infusion; IV or IM administration | |
| Indications | Rescue after high‑dose methotrexate; 5‑FU modulation in colorectal cancer; folate‑deficiency megaloblastic anaemia (with B12 excluded) | |
| Max IV injection rate | 160 mg leucovorin per minute (e.g. 16 mL of 10 mg/mL solution per min) due to calcium load | |
| Typical MTX rescue start | 24 hours after start of methotrexate infusion, then 15 mg (≈10 mg/m²) every 6 hours for 10 doses, adjusted by MTX levels | |
| 5‑FU monthly regimen | 20 mg/m² IV bolus or 200–500 mg/m² over 2 h, followed by 5‑FU 425–370 mg/m² IV bolus for 5 days every 4 weeks | |
| Contraindications | Hypersensitivity, pernicious anaemia or other B12‑deficiency megaloblastic anaemias, intrathecal administration | |
| Key interactions | Antagonism of antifolate antitumor effect if mis‑timed; potentiation of 5‑FU toxicity; reduction of antiepileptic levels (phenytoin, phenobarbital, primidone) | |
| Common adverse effects | Nausea, vomiting, diarrhoea, stomatitis (with 5‑FU), myelosuppression (with 5‑FU), hypersensitivity reactions | |
| Stability after dilution | Stable up to 24 h at 2–8 °C at 0.06–1 mg/mL in common infusion solutions (e.g. 0.9% NaCl, 5% glucose, lactated Ringer’s) |
Clinical practice considerations
In clinical oncology practice, Leucovorin‑Teva 10 mg/mL is embedded in protocol‑driven regimens, with dosing governed by body surface area, methotrexate levels and patient‑specific risk factors for toxicity. Optimal therapeutic use requires multidisciplinary coordination, including oncology, pharmacy and nursing teams, to assure correct timing relative to methotrexate or 5‑FU, avoidance of intrathecal administration, and adherence to stability and compatibility requirements. Continuous pharmacovigilance is warranted, particularly for amplified 5‑FU toxicity and rare but serious hypersensitivity reactions.
This article is intended for educational and informational purposes and does not replace official product information or individual clinical judgement; prescribing and administration should always follow the local Summary of Product Characteristics and institutional protocols for the specific Leucovorin‑Teva presentation in use.













Reviews
There are no reviews yet.